White label telehealth platform is one phrase covering five different products. Some give you software. A few give you clinicians and a pharmacy. None of them give you the medical group, and none of them receive the FDA letter. Here is how to tell them apart. ⚠ Disclaimer: This article is general information for businesses. It is not legal advice and it is not medical advice.
White-label telehealth platform means five different things, and the price range across them runs from about $40 a month to a quarter of a million dollars a year. That is not a market with a wide spread. That is five separate products wearing one label.
The confusion has a cost. An operator signs with a white label vendor, brands the storefront, runs the launch campaign, and then discovers in week three that "white label telehealth" meant a video window and a scheduling calendar. The clinicians were never included. Neither was the pharmacy, the medical group, the merchant account, or the certification that lets you advertise at all.
So before comparing feature lists, sort the white label telehealth market into tiers and work out which one you are actually shopping in. Then ask the question that decides everything downstream, and that almost nobody asks: when something goes wrong, whose name is on the letter?
The five tiers of white label telehealth
These are categories, not brands. Every white label telehealth vendor sits in one of them, and most of them describe themselves using language borrowed from the tier above.
| Tier | What you get | What you still have to supply | Typical published cost | Who it fits |
|---|---|---|---|---|
| Components | A video layer, or an API, or a development agency that will build you software. | The product itself, plus everything clinical. One vendor in this tier states plainly that it does not build prescribing, records or billing. | Usage-based from roughly $0.25 per active user per month, plus mandatory support from $1,000/mo. Custom builds quoted at $40k to $300k+. | Engineering teams. Not operators. |
| Branded software | A real, working, brandable patient experience. Intake, scheduling, video, payments, native apps. | Clinicians, the medical group, state licensure, pharmacy, certification, merchant account. Everything clinical. | Roughly $39 to $75 per user per month, plus a setup fee. Tiers are often counted in your providers, which tells you who is expected to supply them. | A clinic that already has doctors and wants better software. |
| Software plus prescribing plumbing | Branded software plus an EHR and e-prescribing. | Everything clinical except the prescribing software. The pipe exists. Nobody is on the other end of it. | Quote only. Market framings put this at roughly $500 to $2,000 a month. | A practice adding virtual visits. |
| Software plus a clinician network | The tier above plus licensed clinicians, often across all 50 states, with credentialing handled. | The pharmacy. Also usually the merchant account, certification, and the storefront. This is the tier that produces the most disappointment, because the marketing reads as complete. | Quote only. | A brand that already has a pharmacy relationship. |
| Storefront infrastructure | Clinicians, pharmacy, payments, certification support, and a professional corporation, configured before launch. | The brand, the audience, the marketing claims, and the regulatory exposure that attaches to all three. | Where published: setup from about $12,000 with $2,000/mo and a per-consult fee, up to $50,000 setup with $8,000/mo. One platform publishes a flat fee from $297/mo. Most say contact sales. | Operators with an audience and no clinical operation. |
Costs are drawn from vendors that publish list prices on their own pricing pages, checked on 13 August 2026. Most of this market does not publish anything, which is itself a data point.
The clinician network tier is where most of the white label pain lives. A 50-state clinician network sounds like the hard part is solved, and for a primary care or urgent care program it mostly is. For a compounded program it is not, because a prescription is only as useful as the pharmacy that can fill it.
Does a white-label telehealth platform include the doctors?
Sometimes, and it depends entirely on the tier. The honest answer is more useful than the marketing one, because "included clinicians" describes at least three arrangements with very different consequences.

The most common arrangement is that the white label vendor operates its own professional corporation, and the clinicians are employed or contracted by that entity. Read a vendor's telehealth consent form, and you will usually find it: the treating practice named there is the vendor's medical group, not your brand, with the vendor's parent company listed as a third-party beneficiary with rights to enforce the agreement. Your customer signs a document that names a company they have never heard of.
The second is an independent professional corporation that contracts separately with your management company and with the clinicians. The third is a contractor marketplace, which is the weakest of the three, because 1099 status makes the supervision story harder to defend and thin per-consult economics are the exact fact pattern that draws regulatory attention.
None of these gives you the medical group. That is not a vendor failing. In most of the country it is the law.
Why you are not allowed to own the doctors
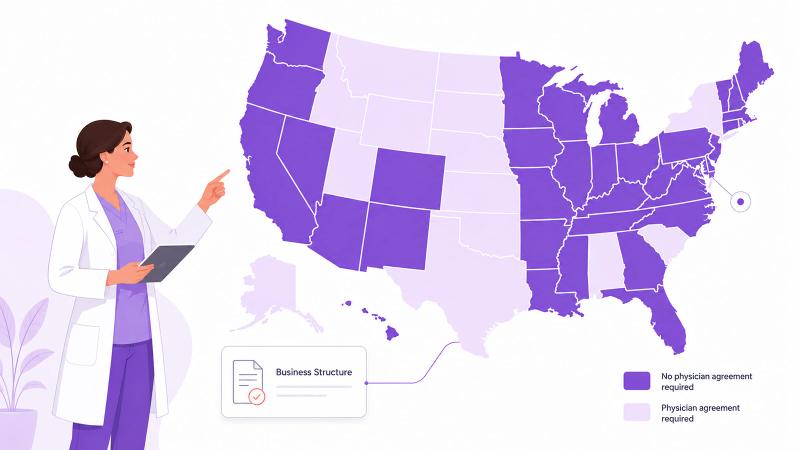
As of a 2024 count, 33 states apply some version of the corporate practice of medicine doctrine, which prevents a general business corporation from employing physicians to deliver care or interfering with clinical judgment. California, Texas, New York and North Carolina enforce it most strictly. Arkansas may be the strictest of all, requiring every officer, director and shareholder of a medical entity to be licensed.
The workaround the whole industry runs on is a professional corporation owned by a licensed physician, contracted to a management services organization owned by the business. The management company handles technology, marketing, billing operations, HR and real estate. The professional corporation keeps clinical protocols, patient selection, the medical record, clinician hiring and firing, scheduling and fee-setting.
That boundary used to be common-law guesswork. Two statutes now write it down. California SB 351 took effect on 1 January 2026 and enumerates what the non-clinical side may not do, including owning or determining the content of medical records. Oregon SB 951 goes further, reaching de facto control, and applies to pre-existing arrangements from 1 January 2029. Vermont enacted similar restrictions effective 1 July 2026.
Enforcement has arrived alongside the statutes. In May 2026, the California Attorney General settled with a dental management company for $2 million. In June 2026, it settled with a healthcare company for $4.4 million, on the Attorney General's own figure, plus a $100,000 penalty against a co-founder personally, over a management agreement that gave the management company authority over advertising, payer negotiations and the hiring, firing and compensation of clinicians. That case was brought under California's general corporate practice statutes, not the newer private-equity law, which means the theory is available against any structure in the state.
For a direct-to-consumer brand, the more pointed precedent is private. In April 2025, Eli Lilly sued two telehealth companies selling compounded tirzepatide, alleging among other things that unlicensed founders and officers influenced dosing and formulation in violation of California's corporate practice rules. The defendants were the consumer brands.
Who gets the letter when a white label program goes wrong
This is the section to read twice, because it inverts what most vendors imply.
On 20 February 2026, the FDA issued a warning letter over compounded GLP-1 marketing. It was addressed to the consumer brand. Not the platform that supplied the software, not the medical group that employed the prescriber, not the pharmacy that filled the order. The brand on the website.
That was not a one-off. Another wave followed in June 2026, and reporting has traced the prescribers behind several of the warned brands back to a small number of nationwide medical groups, all of them white-label infrastructure providers. Same clinical entity, different brand names on the storefronts, and the letters went to the storefronts.
The reason is straightforward once you see it. FDA warning letters in this category are about misbranding and advertising claims. The claims are on your site, in your email flow, in your creator briefs. Your vendor did not write "clinically proven" in your ad copy. You did.
So when a vendor says it handles compliance, ask which compliance. Certification, HIPAA architecture, state licensure and prescribing workflow are genuinely theirs. Marketing claims are genuinely yours, and marketing claims are what the enforcement is actually about.
The pharmacy question decides your white label catalog
Ask any white label telehealth vendor which pharmacies it routes to and what type they are. The answer either opens or closes most of your product line.
A retail mail-order pharmacy dispenses FDA-approved products. That covers branded GLP-1s and a lot of primary care. It does not cover anything compounded. A 503A compounding pharmacy makes patient-specific preparations against a prescription. A 503B outsourcing facility produces batches. If your program involves compounded semaglutide, hormone preparations or peptides, retail mail-order is not a substitute, and no amount of integration work makes it one.
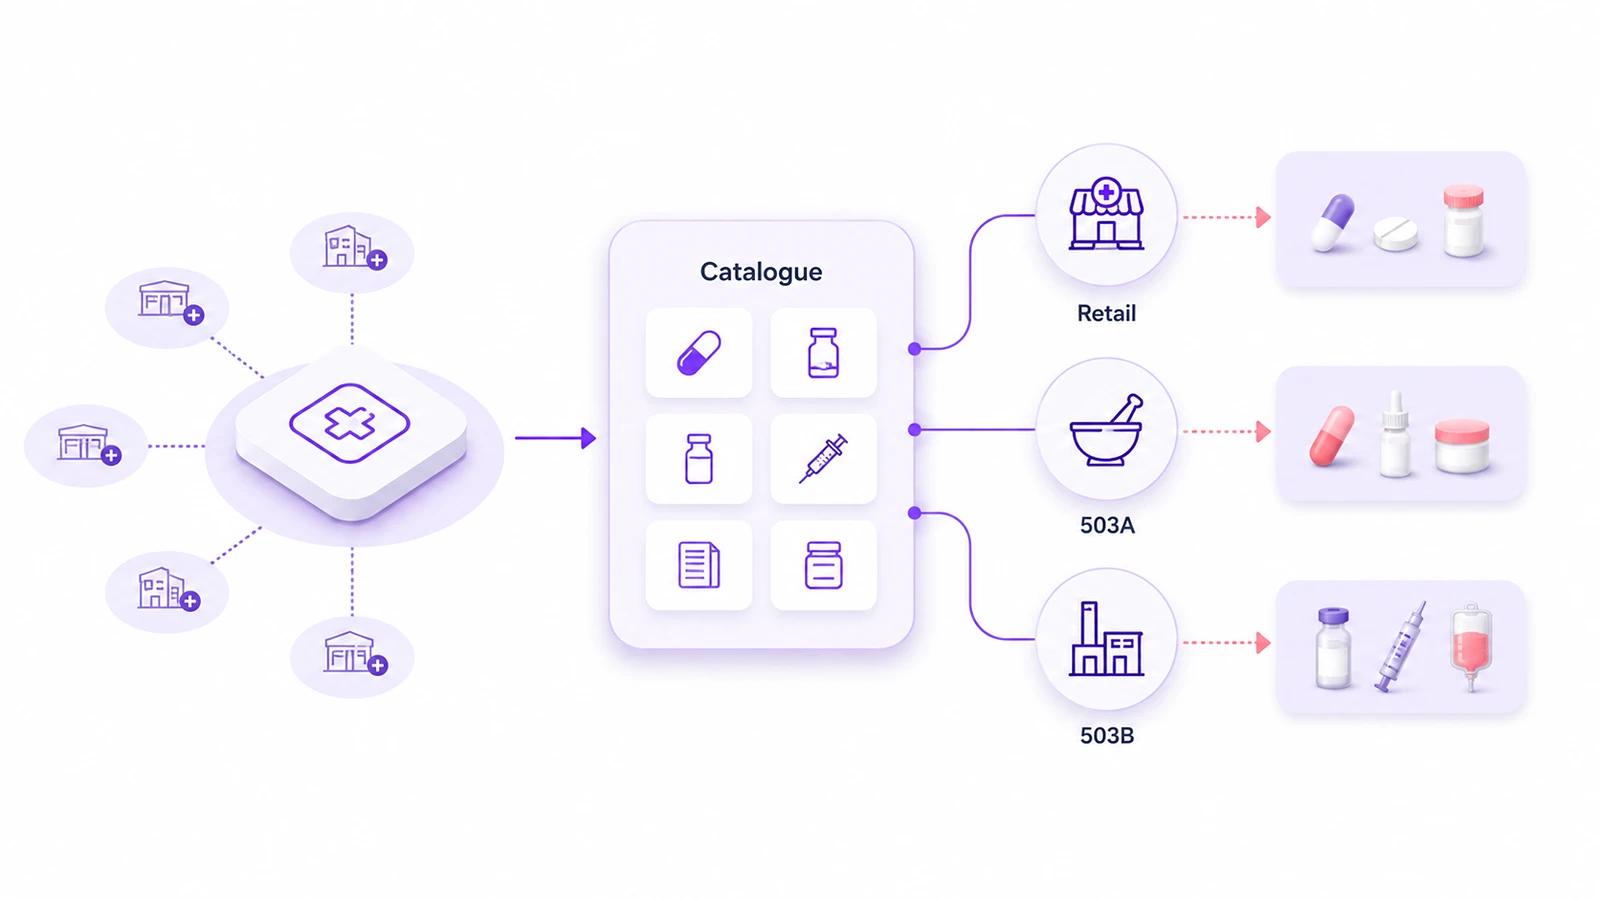
This is where several impressive-looking clinician-network platforms quietly fail. A nationwide clinician network paired with a large retail pharmacy partnership reads like a complete stack, right up until you try to fill something compounded. One vendor in that position publishes its own guide telling buyers to go and select a fulfillment provider themselves, which is at least honest.
Two follow-up questions are worth as much as the first. How many pharmacies, and can you switch? Single-pharmacy dependency is the most common structural weakness in this category, and it fails at the worst possible moment: a capacity ceiling during your best month, a license lapse in a state that happens to be a fifth of your volume, or a partner deciding it no longer wants to compound a category. Our guide to which peptides are legal covers how substance status moves, and why a catalog built on one molecule is fragile.
What a white label telehealth platform costs, and where the $400,000 figure came from
Search for this, and you will be told, confidently, that building custom takes over a year and costs up to $400,000. Google's AI Overview says it. Several vendor blogs say it.
It traces back to a single software outsourcing agency's blog post from July 2025, estimating the cost of building a telemedicine app from scratch by multiplying hours by a blended rate and adding a contingency. A white-label platform vendor repeated it that September. From there, it became a fact. There is no study behind it and no case data.
The number is also measuring the wrong thing. Software is the cheap part. What actually consumes a build budget is the professional corporation, the medical director who will sign your protocols, licensure across the states you sell into, certification, a merchant account that survives underwriting, and pharmacy contracts. None of that appears in an app development estimate.
Here is what white label telehealth platforms actually publish, on their own pricing pages, as of 13 August 2026.
| Model | Published price | What it tells you |
|---|---|---|
| Headless API | $0.25 per monthly active user, e-prescribing $35 to $45 per provider per month, support mandatory in production at $1,000 or $5,000 per month | Priced like cloud infrastructure, because that is what it is. Honest about it. |
| Branded software | About $39 to $75 per user per month plus setup | Per-seat pricing on your providers is the tell that clinicians are not included. |
| Storefront infrastructure, lower tier | About $12,000 setup plus $2,000 per month, plus roughly $25 per completed consult, with no medication markup and no revenue share | The only credible per-consult benchmark in the public domain. |
| Storefront infrastructure, flat fee | From about $297 per month | A newer pricing posture aimed at operators who refuse revenue share. |
| Storefront infrastructure, upper tier | Up to about $50,000 setup plus $8,000 per month | Enterprise configuration. |
| Most of the market | Contact sales | Roughly two thirds of the vendors reviewed publish nothing. Read that as a negotiating position, not a technical constraint. |
One line item is missing from every published price, and it is the one that decides your margin: revenue share. No vendor publishes a percentage. Legal commentary in this category notes that infrastructure providers often take significant fees or a share of revenue. The clearest evidence is indirect but hard to argue with: the newest entrants market explicitly against revenue share, which tells you what they think the incumbent norm is. Ask for the number in writing before you get to a term sheet.
Should you build or buy a telemedicine platform?
For most operators, the honest framing is not build versus buy a telemedicine platform. It is which tier to buy, because almost nobody in this audience is going to recruit a medical director, stand up a professional corporation, and negotiate compounding contracts to save a platform fee.
Build genuinely wins in three situations. You have a clinical requirement no platform covers, which is rare and usually means a novel care model rather than a novel molecule. You have eighteen months of runway and no pressure to show revenue. Or the clinical infrastructure itself is your differentiation and you intend to sell it to others later, which makes you a platform company rather than a brand.
Everywhere else, the arithmetic favors buying, and the reason is not the software cost. It is that the regulatory surface keeps moving. Compounding rules shifted three times in the last eighteen months. Two states rewrote their corporate practice statutes this year. As of August 2026, the DEA telemedicine flexibilities that make hormone programs workable sit on a temporary extension that expires on 31 December 2026, with no replacement rule published yet. A team that builds its own stack now owns the job of tracking all of that forever.
The useful question is narrower: what do you want to be responsible for on a Tuesday in eighteen months? If the answer includes credentialing renewals and pharmacy contract negotiations, build. If it is brand, audience and margin, buy, and buy at the tier that leaves you holding only those three.
Nine questions to ask a white label vendor before you sign
Ask these in writing. The answers separate the white label tiers faster than any feature comparison, and a vendor that will not answer them on paper has told you something.
- Which professional corporation employs or contracts the clinicians, and who owns it? Ask to see the patient consent form your customers will sign.
- Which pharmacies do you route to, what type is each, and can I use more than one? If any part of my catalog is compounded, name the 503A partner.
- Who is the merchant of record, and who carries chargeback risk?
- Do you hold LegitScript certification, help me obtain mine, or is it my responsibility? How long does it take in practice?
- Which states can you actually prescribe in today, for my specific program categories, and where are the gaps?
- What is the total cost, including any revenue share or medication markup, written as a number?
- If I leave, what exactly do I take with me? Get the patient record export right: its format, its cost and its timeline in the contract.
- Do you operate any consumer brands of your own in my category?
- When a regulator writes to someone about my program, who receives the letter, and what do you do next? Ask what happened the last time it occurred.
Question nine is the one that changes the conversation. Everything before it is procurement. That one is about what happens on the worst day.
What to do with this
Take whatever white label telehealth proposal is on your desk and place it on the tier map. If it is components or branded software and you do not already employ clinicians, the gap between what you are buying and what you need is the entire clinical operation. If it is a clinician network, find the pharmacy answer before anything else. If it is storefront infrastructure, go straight to questions one, seven and nine.
FUSE Health sits in the storefront infrastructure tier and we are direct about the boundary. Clinicians, pharmacy routing, payments and certification are configured before you launch. The professional corporation is a real medical group with a real physician owner, and we tell you which one and show you the consent form. You keep the brand, the customer relationship and the margin. What you cannot outsource to us, or to anyone, is what your marketing says, and we would rather say that in a blog post than in a renewal call.
That is the difference between a white label platform you rent and infrastructure that holds. One of them fails quietly in month three. The other one you stop thinking about.
Disclaimer: this is general information for businesses. It is not legal advice and it is not medical advice. Corporate practice of medicine rules, state licensure requirements and federal prescribing flexibilities all change, sometimes quickly. Check the date on this page, and confirm anything you plan to act on with your own counsel.
References
- U.S. Food and Drug Administration, warning letter to MEDVi, LLC, 20 February 2026
- Sheppard Mullin, FDA's Focus Returns to Compounding and Telehealth: Another Wave of Warning Letters, June 2026
- Epstein Becker Green, California Governor Signs SB 351, Strengthening the State's Corporate Practice of Medicine Doctrine, 9 October 2025
- Holland & Knight, An Update on the Implementation and Implications of Oregon's SB 951, 5 May 2026
- Sheppard Mullin, Vermont Enacts Sweeping Restrictions on Private Equity Involvement in Health Care, 29 July 2026
- Sidley Austin, Corporate Practice of Medicine Update: California Attorney General Announces Carbon Health Settlement, 6 July 2026
- DLA Piper, Corporate Practice of Medicine Enforcement, 31 July 2026
- Wilson Sonsini, Telehealth Companies Sued for Selling Compounded GLP-1 Drugs and Violations of Corporate Practice of Medicine Laws, 5 May 2025
- The Source on Healthcare Price & Competition, UC Law San Francisco, Corporate Practice of Medicine, March 2025
- Nelson Mullins, Corporate Practice of Medicine Doctrine: Increased Enforcement on the Horizon, 17 January 2023
- Stevens & Lee, Management Fee Structures and the Corporate Practice of Medicine, 3 August 2026
- HHS Office of Inspector General, Advisory Opinion 25-03, issued 6 June 2025
- Federal Register, Fourth Temporary Extension of COVID-19 Telemedicine Flexibilities for Prescription of Controlled Substances, 90 FR 61301, 31 December 2025
- Interstate Medical Licensure Compact Commission, member state statistics, updated 6 August 2026
- Nurse Licensure Compact, participating jurisdictions
- LegitScript, Healthcare Merchant Certification
- 45 CFR 160.103, 164.501, 164.502(e), 164.504(e) and 164.524, HIPAA covered entity, business associate and record access provisions
- Federal Trade Commission, final order against NextMed, 3 December 2025
- Vendor pricing pages, checked 13 August 2026. Published list prices only.

Daniel is a two-time founder who has scaled service businesses across major U.S. markets. A Y Combinator competition winner, he focuses on removing operational and regulatory barriers so operators can build and scale modern healthcare businesses.
- Background
- Startup Operations & Service Systems
- Experience
- 2x Founder, Multi-Market U.S. Scaling
- Qualifications
- Healthtech Market Expertise & Operational Scaling
- Key Achievement
- Scaled Premier Staff & Eventstaff across major U.S. markets