

Executive Summary
Healthcare automation on a telehealth platform runs the admin work around care: intake, case routing, pharmacy handoffs, refills and billing. The prescribing decision stays with a licensed provider. Get that split right and you can grow from 200 to 5,000 patients without growing an ops team at the same pace.
Disclaimer: This article is general information for business operators. It isn't medical or legal advice. Talk to qualified healthcare counsel before you launch a telehealth program or change a clinical workflow.
If you're launching a GLP-1, TRT or peptide program, you'll hear a lot of platforms promise to "automate everything." Some of that promise is real, and some of it should worry you. This guide walks through what a telehealth platform can run on its own, where the compliance line sits, and what the switch does to your costs per patient.
What Healthcare Automation Covers on a Telehealth Platform
Think of your program in two layers. The operational layer moves information and money from one step to the next. The clinical layer is where a licensed provider makes a medical decision. Healthcare automation belongs in the first layer, and the legal risk starts the moment it creeps into the second.
Workflows a Platform Can Automate
Most of this runs as asynchronous telehealth, meaning the patient and provider don't have to be online at the same time. HHS points to automated online intake as one way to standardize that process.
- Intake forms, identity checks and eligibility pre-screening, finished before a provider opens the case
- Routing each case to the right provider queue by state, program type and availability
- Sending the approved prescription to a partner pharmacy through e-prescribing
- Status updates to the patient when the order is received, shipped and delivered
- Refill triggers tied to the subscription cycle and the program's clinical protocol
- Subscription billing, renewals and automatic retries when a card fails
- Patient re-engagement messages for adherence and program continuation
- HIPAA audit logs that record who touched each record and when
Decisions That Stay With a Licensed Provider
- Reviewing the intake and deciding whether the patient is a fit for the program
- Writing, changing or declining every prescription
- Clinical judgment on contraindications, drug interactions and patient-specific risk
- Any message that counts as clinical advice
A platform can line all of this up so the provider spends their time on the decision itself. It can't make the decision. When a vendor blurs that line, you're the one holding the compliance exposure.
Healthcare Automation vs. Workflow Automation
You'll see both terms in vendor decks. Task automation handles one step, like sending a reminder. Healthcare workflow automation chains steps together with rules, so one event kicks off the next without anyone sitting in the middle.
| Factor | Task automation | Workflow automation |
|---|---|---|
| Scope | One step | A full sequence of steps |
| Example | Send a refill reminder | Refill date hits, provider review request opens, pharmacy order goes out, shipping update follows |
| Logic | Fixed | If/then rules |
| Handoffs | None | Between systems and people |
For a subscription program, workflow automation is the one that pays. A reminder that goes out but never creates the provider review or the pharmacy order still leaves your team doing the real work by hand.

How Healthcare Workflow Automation Works Behind the Scenes
You don't need to be technical to judge a platform, but it helps to know the three parts doing the work.
Triggers and Rules
Every automated step starts with a trigger: a finished intake, an approved prescription, a renewal date or a declined card. Rules decide what happens next. If the intake flags a disqualifying answer, the case reaches the provider with that flag on top. If a payment fails, the retry schedule starts and the patient gets a link to update their card.
Integrations With Pharmacy, Payments and Records
Rules only work when the systems can talk to each other. A telehealth platform connects intake, the provider queue, e-prescribing to the pharmacy and the payment processor, so each piece of data gets entered once. Miss one of those connections and someone on your team becomes the connection, copying order numbers between tabs all day. That's why pharmacy integration needs to be live before your first patient.
Where AI and RPA Fit
Hospital guides spend a lot of time on robotic process automation (RPA), which is software that clicks through old systems the way a person would. Most telehealth programs run on newer systems with direct connections, so you'll rarely need bots. AI is handy for sorting and summarizing, like flagging an incomplete intake or drafting a case summary for the provider to read. The clinical call stays with the provider.
Healthcare Automation Examples Across the Patient Journey
Here's where automation shows up from first click to tenth refill, and who still steps in at each stage.
| Stage | What runs automatically | Who still steps in |
|---|---|---|
| Intake | Branching questions, ID check, eligibility screen | Provider reviews the finished case |
| Case routing | Assignment by state, program and availability | Ops, only for exceptions |
| Prescription | Sent to the partner pharmacy after approval | Provider approves or declines |
| Fulfillment | Order, shipping and delivery updates | Support, for late or lost packages |
| Refill | Trigger on the cycle date, provider review request | Provider re-reviews per protocol |
| Billing | Renewals, retries, card-update messages | Finance, for disputes |
| Retention | Adherence and win-back messages | Marketing writes the content |
Three of these stages carry most of the operational weight. They line up with the five core workflows every telehealth program runs on.
Intake and Eligibility Screening
Manual intake is usually the first thing to break. At a few hundred submissions a day you get half-finished forms, uneven screening and providers chasing missing answers. Branching intake asks condition-specific questions, flags disqualifying answers and screens eligibility before a provider opens the case, so providers get a complete case and you get cleaner data.
Pharmacy Routing and Fulfillment Updates
This is the step that decides retention. The gap between a signed prescription and a shipped order is where patients who meant to stay quietly drop off. Automated pharmacy routing sends the order the moment it's approved, and the patient gets an update at each stage. Your team can see where every order sits without calling the pharmacy.
Refills, Renewals and Failed Payments
Failed payments leak more revenue than most operators expect. A PYMNTS survey of 200 subscription executives, run with FlexPay, found that involuntary churn from failed payments makes up about 50% of all subscription churn, and only 53% of the firms surveyed even track it.
Automated refill triggers, card-update messages and payment retries catch most of these before a patient falls out of the program, with no one on your team chasing them. We cover the margin side in our guide to subscription refills.

What Healthcare Automation Can't Replace
The line between what you can automate and what you can't is a compliance line, so treat it as one when you compare vendors.
Why Prescribing Stays a Human Decision
A licensed provider has to review the patient's information and make an independent judgment before any prescription goes out. Their license sits behind that decision, so a platform can prepare the case but can't sign it.
Plan for that review as a fixed cost in your model. Some platforms charge a fee for every case reviewed; FUSE doesn't charge per visit or per prescription, and the full breakdown is on our pricing page. Automation then brings down the cost of everything around that review.
How to Spot a Risky "Fully Automated" Claim
- Ask who signs each prescription, and ask to see that provider's license details
- Ask what happens when intake answers conflict with each other
- Ask where the automation stops and your responsibility starts
- Ask for the audit log of a sample case
If a vendor says prescribing is fully automated, treat it as a red flag. A sound platform automates everything up to the provider's review and logs everything after it. Our guide to telehealth compliance walks through the five points where workflow design protects you.
HIPAA Controls to Expect in an Automated Stack
| Control | What to check |
|---|---|
| Business associate agreement (BAA) | The platform signs one before any patient data moves |
| Role-based access | Support staff can't open clinical notes they don't need |
| Encryption | Data is encrypted in transit and at rest |
| Audit logs | Every action carries a user and a timestamp, and someone reviews them |
How Healthcare Automation Changes Telehealth Unit Economics
Automation turns a fixed payroll cost into a platform cost that moves with patient volume, so your costs track revenue as it grows.
The Admin Headcount You'd Otherwise Hire
Without automation, someone has to chase intakes, call pharmacies, fix billing exceptions and send refill reminders. Here's what one medical administrative assistant costs per year in five large US metros, based on BLS wage data (annual mean wage, May 2023, before benefits and payroll taxes).
| Metro area | Annual mean wage |
|---|---|
| Los Angeles | $49,970 |
| Boston | $49,660 |
| New York | $48,990 |
| Chicago | $44,260 |
| Dallas-Fort Worth | $42,280 |
| US average | $43,380 |
If a manually run program needs two or three of these roles for every 1,000 active patients (your ratio will depend on the program), that's roughly $85,000 to $150,000 a year in wages alone in these metros. And that cost stays put whether your active count dips to 800 or climbs to 1,200.
What Changes at 200, 1,000 and 5,000 Patients
- At 200 patients, manual operations are annoying but manageable
- At 1,000 patients, ops work becomes the main limit on margin
- At 5,000 patients, manual processes become the main point of failure
Building on automated infrastructure early means you don't have to rebuild operations in the middle of growth. We break down the payback math in our piece on automation ROI.
What CAQH Data Shows About Healthcare Admin Costs
Automation in healthcare is moving the same way across payers and providers. The 2025 CAQH Index estimates US healthcare avoided $258 billion in administrative costs in 2024 through electronic transactions, and still sees a $21 billion savings opportunity in steps that remain fully or partly manual.
How to Roll Out Healthcare Automation in a Telehealth Program
Whatever clinic workflow automation tools you're comparing, roll them out in this order.
Map How Your Workflow Runs Today
Write down every step from intake to refill, who owns it and how long it takes. Most operators find at least one step that three different people touch.
Automate Pharmacy Routing and Refills First
Start where a delay costs you a patient. Routing and refills are high volume, rule-based and tied straight to retention. Intake branching comes next, then retention messaging.
Track Four Numbers Before and After
- Intake completion rate
- Time from provider approval to shipment
- Share of refills processed on time
- Failed payment recovery rate
Write the baseline down before you switch anything on. Nobody remembers it afterward.
Healthcare Automation in FUSE Health
What FUSE Automates Out of the Box
FUSE Health runs the operational layer for you: intake and case routing, prescription transmission to partner pharmacies, fulfillment updates, subscription billing and renewals, refill triggers you configure before launch, and adherence messages. It's the same infrastructure behind every white-label telehealth brand on the platform.
What FUSE's Licensed Provider Network Handles
Every case is reviewed by a licensed provider in the FUSE network. That review stays human by design, and you can see exactly where your responsibility starts and ends. If you're already past a few thousand patients, here's how the setup works for high-volume operators.
When you compare platforms, ask three questions: what's automated, what licensed providers handle, and where your responsibility starts. A platform that answers all three clearly is one you can scale on.
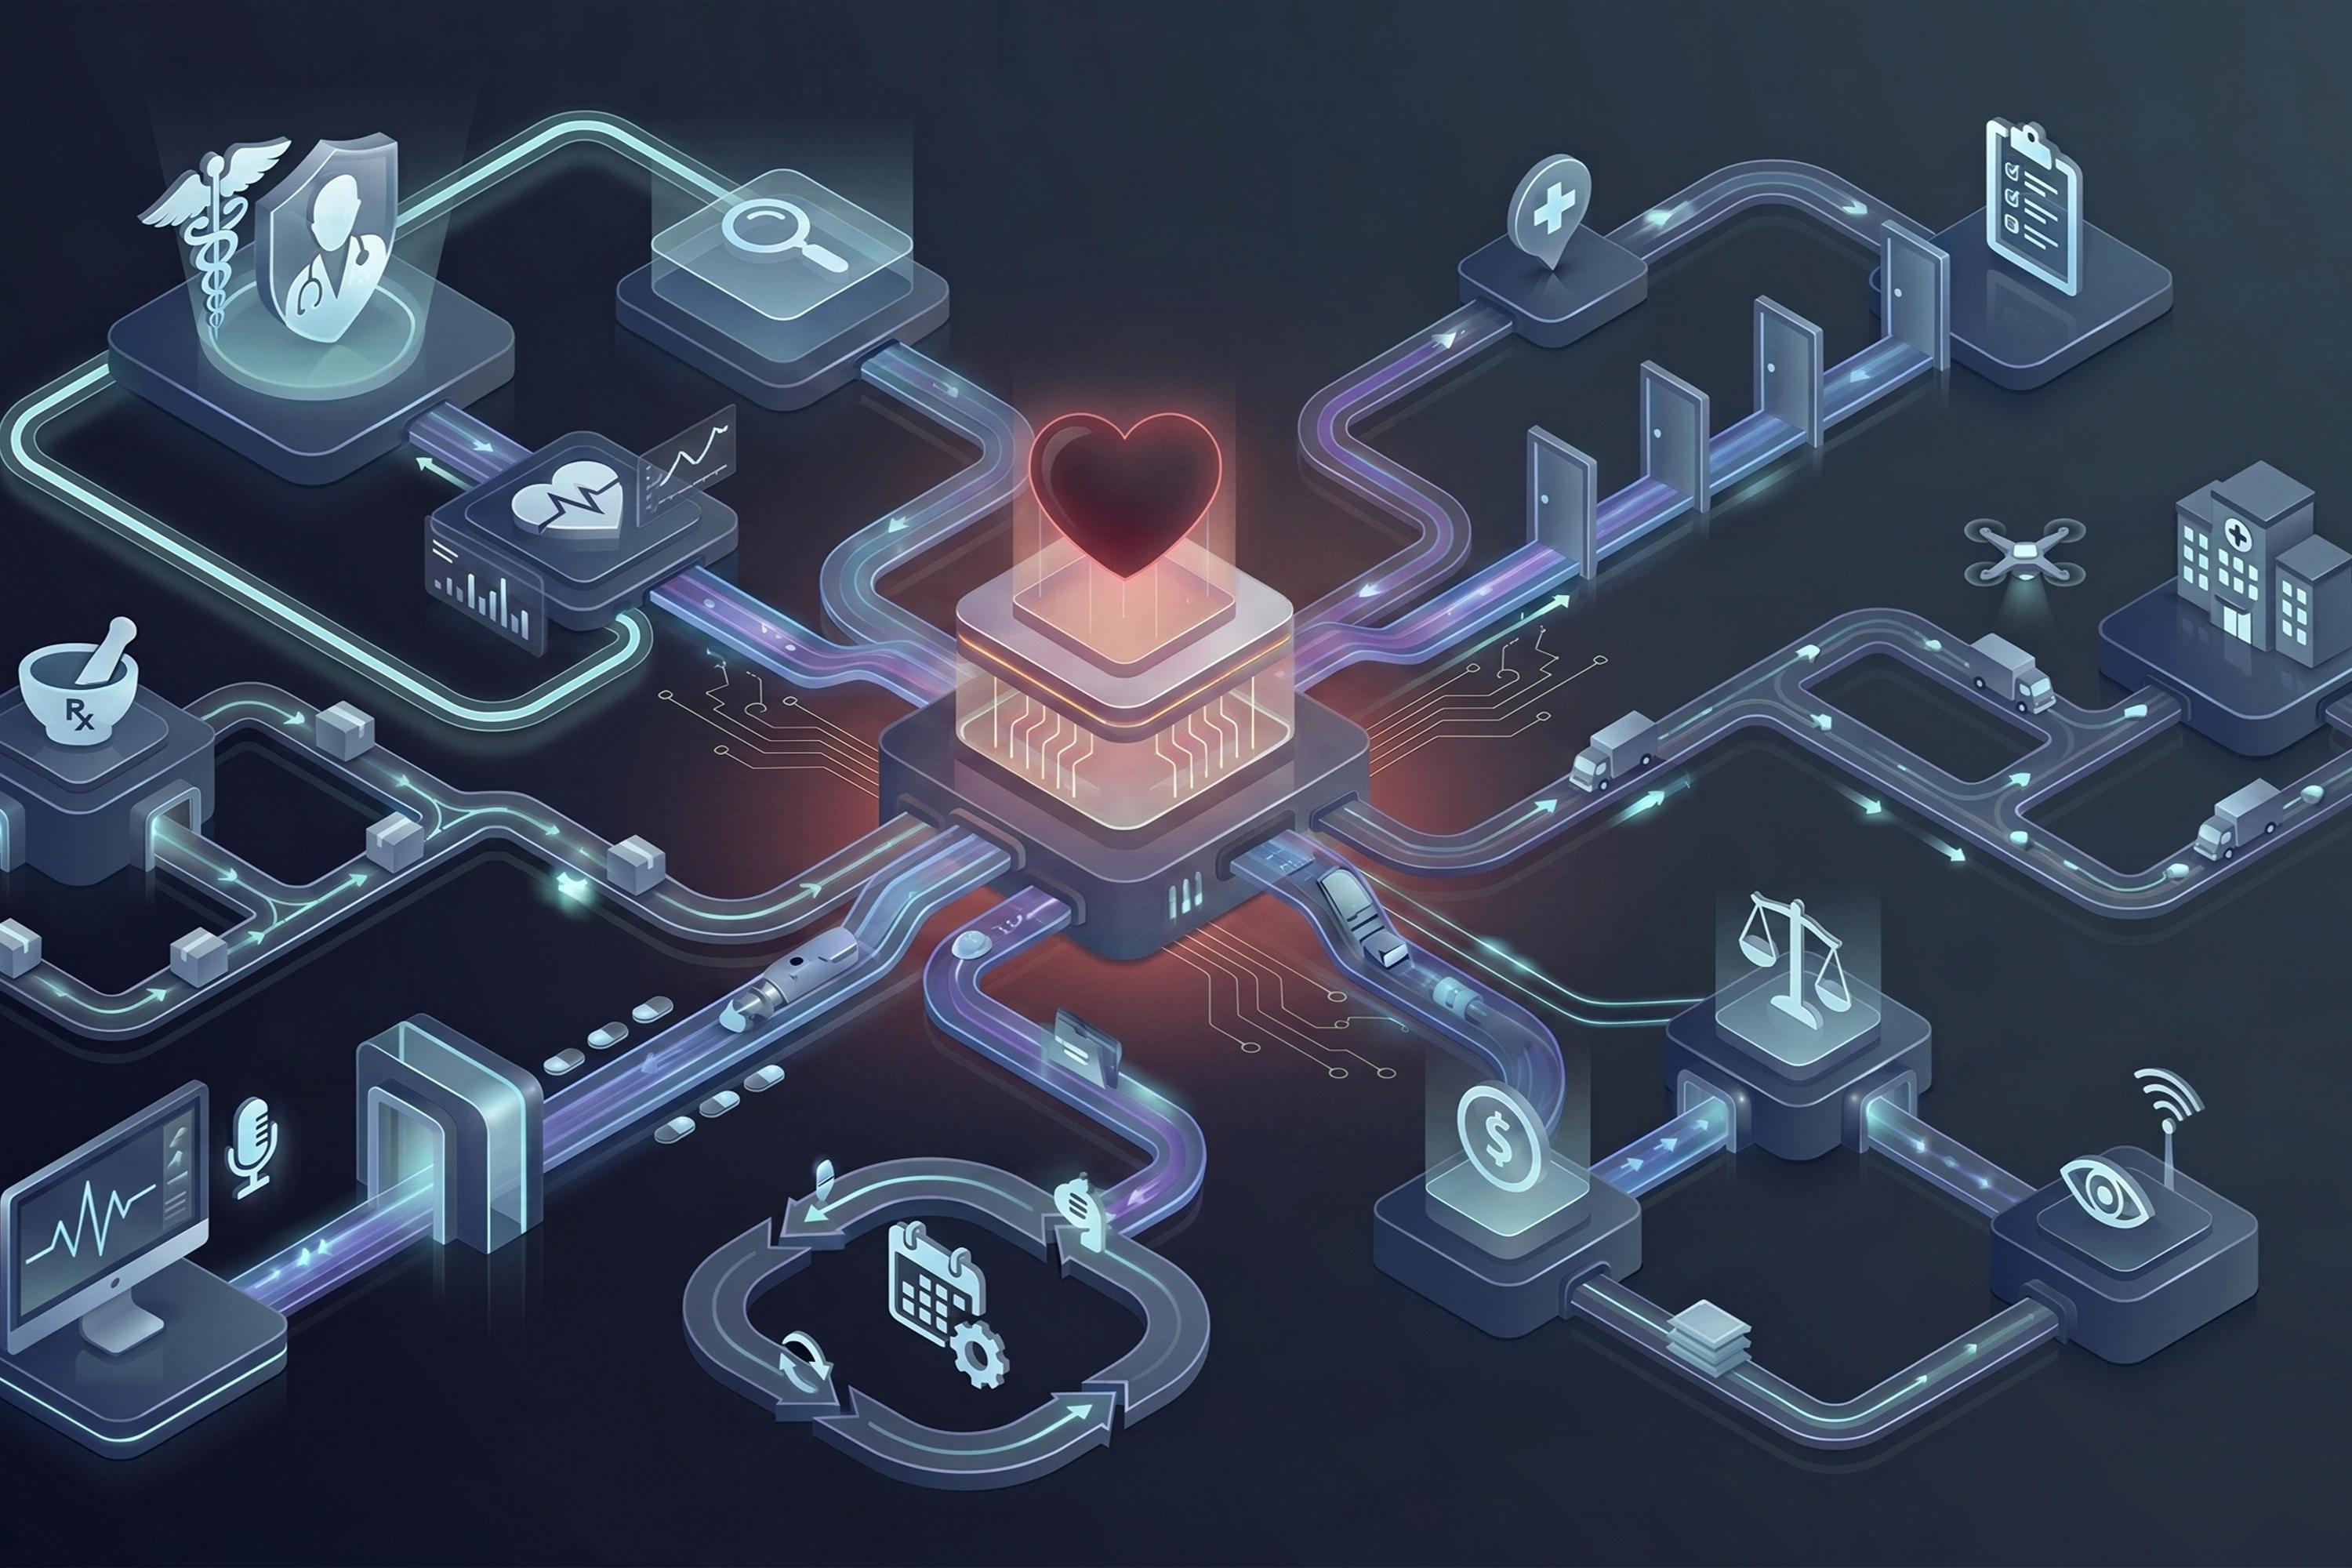
Building a Telehealth Program That Scales With Healthcare Automation
Healthcare automation decides whether a telehealth program grows into profit or stalls under its own admin load. The programs that grow revenue without growing headcount automate intake, fulfillment, billing and renewals, and keep a licensed provider in charge of every prescription.
FUSE Health gives non-clinical operators that setup from day one. The operational layer runs on its own, licensed providers handle the clinical layer, and your team stays focused on brand and acquisition. If you want to launch on infrastructure that's ready for your thousandth patient, see how FUSE works and book your walkthrough.
References
- [1] U.S. Department of Health and Human Services, "Asynchronous direct-to-consumer telehealth," telehealth.hhs.gov
- [2] PYMNTS and FlexPay, "Avoidable Failed Payments Cause 50% of Subscription Churn," PYMNTS.com, 2023
- [3] CAQH (Dataspring), "2025 CAQH Index Shows U.S. Healthcare Avoided $258 Billion," 2025
- [4] U.S. Bureau of Labor Statistics, Occupational Employment and Wages, May 2023: Medical Secretaries and Administrative Assistants (43-6013)

Daniel is a two-time founder who has scaled service businesses across major U.S. markets. A Y Combinator competition winner, he focuses on removing operational and regulatory barriers so operators can build and scale modern healthcare businesses.
- Background
- Startup Operations & Service Systems
- Experience
- 2x Founder, Multi-Market U.S. Scaling
- Qualifications
- Healthtech Market Expertise & Operational Scaling
- Key Achievement
- Scaled Premier Staff & Eventstaff across major U.S. markets



